How Long Should You Give an Elimination Diet Before Deciding?
Quick Answer: Two to six weeks of elimination is enough for almost everyone - typically two to four weeks for a single food, and four to six for a structured protocol like low FODMAP. Longer is not better and carries real costs. The part that matters is the reintroduction phase, which most people skip: reintroduce one food at a time, in increasing amounts over three days, with at least three symptom-free days between tests. Without that, you have not learned anything - you have just narrowed your diet.
An elimination diet is a diagnostic test, not a way of eating. The single most common mistake is treating the elimination phase as the destination.


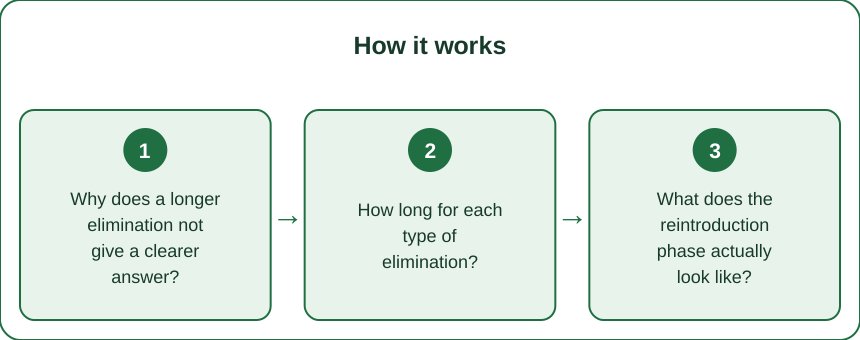
Why does a longer elimination not give a clearer answer?
Because the symptom improvement plateaus quickly and everything after that is noise. If removing a food is going to help, the great majority of the improvement appears within two to four weeks.
After that you start losing information rather than gaining it. The longer you avoid a food, the harder it becomes to attribute anything to it, because life changes in the meantime - stress, sleep, seasons, other dietary shifts.
There are real costs to a long elimination. Restrictive diets reduce fibre and dietary diversity, which affects the gut microbiome directly. A structured protocol like low FODMAP measurably reduces beneficial bacterial populations when extended, which is precisely why the clinical protocol is time-limited.
There is a nutritional cost too. Long-term dairy exclusion without replacement affects calcium; long-term grain exclusion affects fibre and B vitamins.
And there is a psychological cost that is easy to underestimate. Extended restriction narrows what feels safe to eat, and for some people that trajectory becomes a bigger problem than the original symptoms.
So the discipline is to set the window before you start, and to hold yourself to reintroducing on schedule even if you feel good. Especially if you feel good.
How long for each type of elimination?
A single suspected food: two to four weeks. Dairy, eggs, a specific fruit. That is comfortably long enough to see a clear effect.
Low FODMAP: two to six weeks of the restriction phase, and no longer. The published protocol is explicit that this is a short diagnostic phase followed by a structured reintroduction over six to eight weeks. It is not a long-term diet, and the majority of people who follow it end up tolerating most FODMAP groups.
Gluten: this one has a critical exception. Do not remove gluten before being tested for coeliac disease. Coeliac testing requires you to be eating gluten regularly, and going gluten-free first makes the test unreliable and may mean you have to reintroduce it for weeks to be tested properly. See a doctor before cutting gluten, not after.
Caffeine or alcohol: two weeks is usually enough, though caffeine has a withdrawal period of about a week that muddies the first days.
Broad multi-food eliminations: only under professional supervision. Cutting several major food groups at once is where nutritional gaps and disordered patterns appear, and it also makes the results uninterpretable, since you cannot tell which removal did what.
And symptoms with an obvious cycle need longer. If your symptoms vary with your menstrual cycle, a two-week test tells you very little - run it across a full cycle at minimum.
What does the reintroduction phase actually look like?
One food at a time. This is not negotiable if you want a usable answer.
Test over three days with increasing amounts. Day one a small portion, day two a moderate portion, day three a large portion. Many intolerances are dose-dependent, and a single small test portion tells you nothing about the amount you would actually eat.
Then wait at least three symptom-free days before the next test. Symptoms can be delayed by 24 to 72 hours, and testing back to back means you cannot tell which food caused what.
Test the food in isolation and in a simple form. Testing dairy with a slice of pizza tests dairy, wheat, fat, and portion size simultaneously. Test it with plain milk or plain yoghurt.
Keep the rest of your diet identical during a test. This is the part people find tedious and it is what makes the result trustworthy.
Record symptoms on a simple scale rather than in prose. A 0 to 10 rating for the two or three symptoms you care about, recorded at the same times each day, is far more interpretable a month later than diary entries.
And if a test is positive, stop, wait until symptoms fully settle, then continue with the next food. Do not chain tests through an ongoing flare - everything after that point is uninterpretable.

5 Mistakes That Waste the Whole Exercise
1. Never reintroducing. By far the most common. You feel better, you assume the food is the culprit, and you avoid it indefinitely without ever confirming it. Many of these avoidances turn out to be wrong.
2. Changing several things at once. Cutting dairy, starting a probiotic, and going to bed earlier in the same week means you learn nothing about any of them.
3. Not accounting for the placebo effect and regression to the mean. People start elimination diets when symptoms are at their worst, and symptoms that are at their worst tend to improve regardless. This is why reintroduction matters so much - it is the control condition.
4. Testing a food inside a complex meal. The third mistake catches out even careful people: they reintroduce wheat as a sandwich with cheese and end up unable to attribute the result to anything.
5. Cutting gluten before coeliac testing. This one has consequences beyond a wasted experiment - it can delay a real diagnosis by months and require a deliberate gluten challenge to correct.
A sixth worth naming: ignoring stress, sleep, and routine. Gut symptoms track all three strongly, and an elimination started during a calm fortnight and reintroduced during a chaotic one produces a false positive.
What if nothing improves, or everything seems to be a trigger?
If nothing improves in four weeks, the food was probably not the problem. Reintroduce it and stop. That is a useful negative result, not a failure.
If everything seems to trigger symptoms, that pattern itself is informative and it usually points away from specific food intolerance. Visceral hypersensitivity, stress, meal timing, eating speed, and swallowed air all produce symptoms that appear to correlate with food because food is when you notice them.
Look at how you eat before you look further at what you eat. Meal regularity, eating speed, portion size, and fluid intake with meals change symptoms substantially for many people and cost nothing to test.
Take red flag symptoms to a doctor rather than into another elimination. Unintended weight loss, blood in stool, persistent vomiting, difficulty swallowing, waking at night with symptoms, anaemia, or a family history of bowel disease all need proper assessment, and no elimination diet is the right response to them.
Consider working with a dietitian for anything beyond a simple single-food test. Low FODMAP in particular has a much higher success rate with professional guidance, largely because the reintroduction phase actually gets done.
And be aware of the season. Autumn shifts diet substantially - more cooked food, more legumes and brassicas, fewer cold meals, different routines - and an elimination that starts in early September is running against a moving baseline. If you can, either start it before the shift or wait until your eating pattern has settled into its autumn shape.
This is general information, not medical advice.
FAQ: Elimination Diets, Answered
How long until I know if cutting a food is working?
Usually two to four weeks. If there is no change at all by four weeks, that food is unlikely to be your problem.
Do I have to reintroduce if I feel better?
If you want to know whether the food was actually responsible, yes. Feeling better during elimination is not evidence on its own - improvement happens for many reasons, which is exactly what reintroduction controls for.
What if symptoms come back months later?
Retest properly rather than re-cutting on suspicion. Tolerance genuinely changes, particularly after gut infections or antibiotics, and it also improves - a food that caused problems two years ago may be fine now.
Is low FODMAP meant to be permanent?
No. The restriction phase is two to six weeks, followed by structured reintroduction. Most people end up tolerating the majority of FODMAP groups, and staying on the restriction phase long-term is a recognised problem rather than a goal.
Should I get a food intolerance blood test instead?
Commercial IgG food intolerance tests are not supported by evidence and produce long lists of foods most people tolerate fine. A careful elimination and reintroduction, ideally with a dietitian, remains the reliable approach.
TL;DR:
- Two to four weeks for a single food, four to six for low FODMAP - longer does not clarify anything and costs fibre, diversity, and nutrients.
- The reintroduction phase is the actual test, and skipping it is the most common mistake by a wide margin.
- Reintroduce one food at a time, over three days in increasing amounts, with three symptom-free days between tests.
- Test foods in simple isolated form, and never chain tests through an ongoing flare.
- Do not cut gluten before coeliac testing - it makes the test unreliable and can delay a real diagnosis.
This is general information, not medical advice. Red flag symptoms - weight loss, blood, persistent vomiting, night waking - need a doctor, not another elimination.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
